Dr. Amanda Foster

Up to 70% of dogs with chronic gastrointestinal symptoms that don’t resolve after basic treatment end up with an IBD diagnosis. That number stopped me cold the first time I read it in a clinical gastroenterology review, because I had spent years assuming IBD in dogs was relatively rare. It isn’t. It’s one of the most underdiagnosed and mismanaged conditions I see discussed in online pet communities, and honestly, the amount of conflicting information out there makes a complicated situation worse.
So let’s cut through it.
If your dog has had recurring vomiting, chronic diarrhea, weight loss, or a persistently poor coat for more than a few weeks, IBD is on the table. Not the only possibility, but definitely on the table. And what most people don’t realize is that IBD isn’t a single disease. It’s a category. An umbrella term for a group of chronic inflammatory conditions affecting the GI tract, each with different characteristics and, critically, different treatment approaches.
- IBD in dogs is diagnosed via intestinal biopsy, not bloodwork alone, imaging and labs support but can't confirm it.
- The most common form, lymphocytic-plasmacytic enteritis, often responds well to dietary change before steroids are tried.
- Protein-losing enteropathy, a severe IBD complication, carries a guarded prognosis; early diagnosis dramatically improves outcomes.
- Treatment costs typically run $800–$3,000+ for initial workup; ongoing management averages $50–$200/month depending on medications.
- German Shepherds, Basenjis, Shar-Peis, and Soft-Coated Wheaten Terriers are statistically overrepresented in IBD diagnoses.
What IBD Actually Is (and Isn’t)
Here’s where I want to push back on something I hear a lot: people treating IBD as if it’s basically the same thing as a sensitive stomach. It isn’t. A sensitive stomach means your Labrador barfs when he gets into the trash. IBD means the immune system is actively and persistently attacking the gastrointestinal lining, causing structural changes to the tissue that can be seen under a microscope.
The main subtypes are classified by which immune cells are doing the damage. Lymphocytic-plasmacytic enteritis is the most common by far. Eosinophilic gastroenteritis tends to be more severe and is sometimes linked to dietary antigens. Granulomatous disease is rarer and can be harder to manage. Then there’s protein-losing enteropathy (PLE), which is not a separate type but a serious complication where the inflamed gut leaks protein into the intestinal lumen faster than the dog can replace it. I’ve seen PLE cases come in where the dog looks like it’s starving, despite eating, because the intestine literally can’t hold onto nutrients. That’s the version that scares me most in practice.
What IBD is NOT: it’s not the same as irritable bowel syndrome (IBS, which is a functional disorder), and it’s not the same as intestinal lymphoma, although the two can look nearly identical on biopsy. This distinction matters enormously for treatment. A 2021 paper in the Journal of Veterinary Internal Medicine noted that distinguishing IBD from small cell lymphoma in cats (and the same challenge applies in dogs) sometimes requires advanced immunohistochemistry staining that not every pathology lab automatically runs. Ask specifically if your biopsy is being evaluated with PARR (PCR for antigen receptor rearrangements) if lymphoma is on the differential.
Getting to a Diagnosis
Helpful resource: Thundershirt Classic Dog Anxiety Jacket is a top-rated option for this. (As an Amazon Associate this site earns from qualifying purchases.)
This is where most owners get frustrated, and I don’t blame them. IBD requires ruling out a long list of other causes first: intestinal parasites, bacterial infections like Clostridium or Salmonella, dietary intolerance, exocrine pancreatic insufficiency, hypoadrenocorticism, and others. The workup is sequential and can feel slow.
The definitive diagnosis requires intestinal biopsy. Full stop. Bloodwork, urinalysis, fecal testing, and imaging (ultrasound, specifically) all contribute valuable information, but none of them confirm IBD. Ultrasound can show thickening of intestinal wall layers and changes to the muscularis that suggest inflammatory disease, and an experienced internist reading a GI ultrasound can give you a strong suspicion. But “strong suspicion” is not the same as a tissue diagnosis, and the treatment decisions that follow are significantly different enough that guessing wrong is costly.
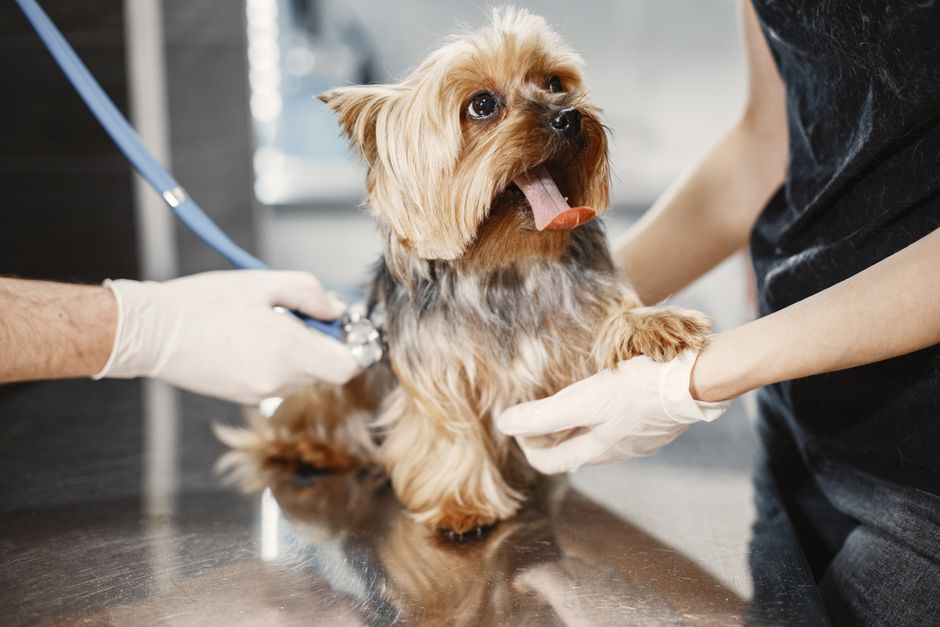
Biopsies are collected either via endoscopy (less invasive, but only reaches the stomach, duodenum, ileum, and colon) or full surgical laparotomy (reaches the entire GI tract including jejunum, and allows full-thickness samples). What most people don’t realize: endoscopic biopsies are mucosal only, meaning they capture the surface layer. Some forms of IBD, particularly those affecting deeper tissue layers, can be missed or undergraded. I’ve seen cases where endoscopy looked mild and surgery revealed something far more significant.
Here’s a practical comparison of the diagnostic path and what to expect:
| Diagnostic Step | What It Rules Out / Confirms | Typical Cost Range (2026) | Turnaround |
|---|---|---|---|
| Fecal panel (PCR-based) | Parasites, bacterial pathogens | $80–$150 | 3–5 days |
| Bloodwork (CBC, chemistry, B12, folate) | EPI, Addison’s, systemic disease, malabsorption | $150–$300 | 1–2 days |
| Abdominal ultrasound | Wall thickening, masses, lymph node changes | $300–$600 | Same day |
| Endoscopy + mucosal biopsy | Surface inflammation, confirms IBD in most cases | $800–$1,800 | 7–14 days for path results |
| Surgical biopsy (full-thickness) | Deep-layer disease, distinguishes IBD from lymphoma more reliably | $1,500–$3,500 | 7–14 days for path results |
| PARR testing (add-on to biopsy) | Differentiates IBD from small-cell lymphoma | $200–$400 additional | 2–3 weeks |
Current as of July 2026; costs vary significantly by region and whether you’re at a GP or specialty/internal medicine practice.
Treatment: Diet First, Then Drugs
I’ll be direct here: the reflex to start steroids immediately is something I’ve seen cause problems. Not because steroids are wrong, they’re often necessary and life-changing for these dogs, but because a significant subset of dogs with IBD respond to dietary management alone, and if you start prednisone before trying an elimination diet, you’ll never know which one actually worked.
The current standard of care (supported by guidelines from the World Small Animal Veterinary Association’s GI Standardization Group) recommends trying one of two dietary approaches for 4–8 weeks before adding immunosuppression in dogs with mild-to-moderate disease:
Hydrolyzed protein diets use proteins that have been broken down to a molecular weight small enough to avoid triggering an immune response. Royal Canin Hydrolyzed Protein and Purina Pro Plan HA are the two I see used most commonly in practice. They’re not cheap, typically $80–$120 for a medium-sized bag, but they’re worth trying before committing to lifelong medication.
Novel protein diets use a protein source the dog has genuinely never encountered: rabbit, kangaroo, venison, duck. The catch is that “novel” only works if it’s truly novel, meaning you have to think back through everything your dog has eaten in the last two years. I tested this approach with a 4-year-old Wheaten Terrier patient who’d been on a rotating protein schedule (great idea in theory, terrible for IBD diagnostics), and we had a genuinely hard time finding something she hadn’t been exposed to. We ended up on kangaroo. Eight weeks later, her albumin had climbed from 1.8 to 2.6 g/dL and her owner reported the first formed stools in months.
When diet doesn’t get the job done, or when the disease is moderate-to-severe at presentation, immunosuppression comes in. Prednisone is first-line, typically started at 1–2 mg/kg/day and tapered over months. For dogs that don’t tolerate pred well (and some absolutely don’t, the panting, the water-drinking, the personality changes can be dramatic), chlorambucil or azathioprine are common second-line options. Cyclosporine is used as well, though it’s considerably more expensive.
Cobalamin (vitamin B12) supplementation is something that gets missed surprisingly often. The inflamed ileum can’t absorb B12 properly, and deficient dogs don’t respond to other treatments as well. If your dog’s folate is high and B12 is low, that pattern specifically points to disease in the small intestine. PetMD’s veterinary resource library has a solid breakdown of this if you want to dig into the GI absorption physiology.
One thing I’d push back on: the idea that IBD dogs need to be on steroids forever. Many dogs, after a year or more of good management, can be weaned off completely or maintained on very low doses. It takes patience and a vet willing to try the taper.
When It Becomes an Emergency
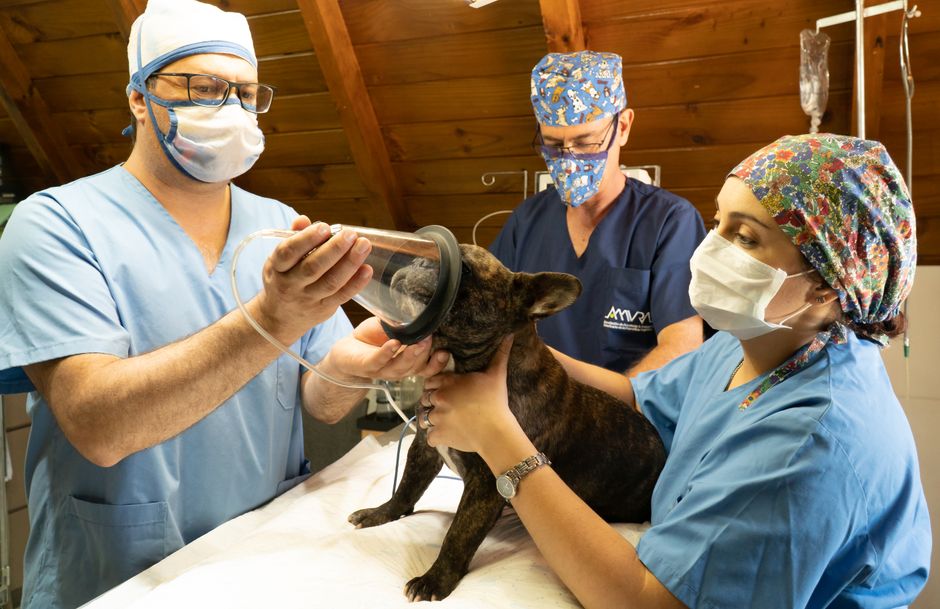
Protein-losing enteropathy is the scenario where we shift from “manage this carefully at home” to “this dog needs to be hospitalized.” Clinical signs that should send you to an emergency clinic: sudden severe swelling of the limbs or abdomen (third-spacing from low albumin), profound lethargy, refusal to eat for more than 36–48 hours in a dog already diagnosed with IBD, or bloody diarrhea with weakness.
The ASPCA Poison Control Center’s database is not the right resource for GI emergencies, but I mention it because some owners accidentally call them when their dog has eaten something they’re unsure about layered on top of existing IBD. If your dog has known IBD and has ingested something potentially toxic, that combination warrants a direct call to an ER vet, not a poison hotline first.
A real case: a 7-year-old Soft-Coated Wheaten Terrier came into a clinic I was working at with an albumin of 1.1 g/dL, bilateral pitting edema, and a body weight 18% below his previous visit four months earlier. The owner had been managing mild IBD with a hydrolyzed diet for two years successfully. What changed: he’d gotten into the neighbor’s compost bin twice and developed a secondary bacterial enteritis on top of the IBD. Rapid deterioration. He spent five days hospitalized on IV colloids, antibiotics, and aggressive nutritional support before he was stable enough to go home. Total bill: just over $4,200. He recovered fully, but it was close.
Living With an IBD Dog Long-Term
Honestly, most IBD dogs do okay. Not perfectly, but okay. Flares happen. Stress triggers them, dietary indiscretion triggers them, sometimes nothing triggers them and it just happens. What separates the dogs that do well long-term from the ones that don’t is usually consistency: consistent diet, consistent monitoring, and an owner who knows their dog’s baseline well enough to catch a flare early.
Keep a simple log. Weight every two weeks at home (you can get a decent baby scale for under $40 that works for small-to-medium dogs). Stool consistency scored 1–7 using the Purina Fecal Scoring System, which your vet can print for you. Appetite on a simple 1–3 scale. This kind of data is genuinely useful at recheck appointments and has, in my experience, led to faster medication adjustments because we’re not guessing from memory.
For dogs on long-term steroids, get a baseline urinalysis and consider a urine culture before each annual bloodwork cycle, because steroid-associated urinary tract infections are common and often silent. A lot of owners don’t know about that one.
If your dog is on chlorambucil, be careful handling the pills. Wear gloves. This is a chemotherapy drug, and while the doses used for IBD are low, chronic skin exposure for the human administering it isn’t a great idea. I’ve seen this instruction left out of discharge paperwork, which is not okay.
Joint supplements like fish oil may have mild anti-inflammatory benefits for GI disease, and there’s some early evidence supporting omega-3 fatty acids in IBD management, though the data in dogs specifically is still thin. I don’t have good numbers on the magnitude of benefit, so I can’t promise anything there. What I can say is that if your dog tolerates them, the risk is low.
Sources
- [Journal of Veterinary Internal Medicine (2021)]: Study on differentiating IBD from small cell lymphoma using advanced immunohistochemistry and PARR testing in companion animals.
- [World Small Animal Veterinary Association GI Standardization Group]: Published guidelines on diagnosis and treatment of chronic enteropathies in dogs, including dietary trial recommendations.
- [Washabau RJ, et al. “Endoscopic, Biopsy, and Histopathologic Guidelines for the Evaluation of Gastrointestinal Inflammation in Companion Animals.” JVIM 2010]: Landmark consensus paper establishing biopsy criteria still referenced in clinical practice.
- PetMD Veterinary Resource Library: Accessible summaries of B12 malabsorption patterns and GI disease in dogs, useful for client education.
- [Marks SL, et al. “Enteropathogenic Bacteria in Dogs and Cats.” JVIM 2011]: Reference on ruling out infectious causes before IBD workup, relevant to the diagnostic sequencing discussed above.
Photo: Andres Ayrton via Pexels
This article is for general informational purposes only and does not constitute veterinary advice. Pet health symptoms can have many causes and require professional evaluation. Always consult a licensed veterinarian for diagnosis and treatment specific to your pet.
Recommended Resources
Disclosure: As an Amazon Associate, we earn a small commission from qualifying purchases at no extra cost to you. We only recommend products that genuinely support the topics covered in this article.
- EVERLIT 95-Piece Vet-Approved Pet First Aid Kit (~$32), Vet-approved 95-piece kit for dogs and cats, covers cuts, burns, sprains, and emergencies until you can reach a vet.
- Nutramax Cosequin DS Joint Supplement for Dogs (132ct) (~$36), The #1 veterinarian-recommended joint supplement brand, clinically studied for reducing joint pain in dogs.