James Whitfield

Most people who find a lump on their dog assume it’s a lipoma. A fatty lump, harmless, something to watch. I made that assumption once myself, back in my early years at the clinic, when a client brought in her seven-year-old Boxer with a small, soft swelling on his flank. “Probably nothing,” I almost said. Then I caught myself, aspirated it, and found mast cells under the microscope. That dog had a Grade II mast cell tumor. He made it, thankfully, but it was a hard lesson in why “probably nothing” is a dangerous phrase.
Mast cell tumors (MCTs) are the most common malignant skin tumor in dogs, accounting for somewhere between 16 and 21 percent of all skin tumors diagnosed. They can look like anything: a raised pink nodule, a flat welt, a soft lump that’s been there for months without changing. That’s what makes them genuinely tricky. There’s no reliable way to look at a skin mass and rule out mast cell disease. None. The only way to know is to sample it, and that matters more than almost anything else I could tell you in this article.
What surprised me, when I went deeper into the literature a few years back, is how dramatically outcomes vary depending on grade, location, and treatment timing. This isn’t a death sentence. For many dogs, it’s a manageable, even curable, disease. But you need to understand the landscape of this diagnosis to make good decisions for your dog.
- Mast cell tumors are the most common malignant skin tumor in dogs; any new lump needs a fine needle aspirate, not a wait-and-see approach.
- Grade I and II tumors have good to excellent prognoses with complete surgical removal; Grade III tumors require aggressive multimodal treatment.
- Boxers, Boston Terriers, Bulldogs, and Pugs are genetically predisposed; any lump on these breeds warrants faster action.
- Systemic signs like vomiting, stomach ulcers, or facial swelling alongside a lump are red flags for high-grade or metastatic disease.
- Toceranib phosphate (Palladia) changed the treatment options for inoperable MCTs starting around 2009 and remains a standard tool today.
What Is Actually Happening Inside That Tumor
Mast cells are normal immune cells. They live in your dog’s connective tissue, skin, and respiratory tract, and they carry granules loaded with histamine, heparin, and other inflammatory mediators. In a mast cell tumor, those cells proliferate abnormally and those granules become a problem, because MCTs can degranulate, releasing a flood of histamine and other chemicals into the body.
This is why mast cell tumors aren’t just a “skin thing.” A large or aggressively degranulating tumor can cause systemic effects: gastric ulcers (histamine drives excess stomach acid production), vomiting, internal bleeding, hypotension during surgery. There’s a reason surgical teams handling MCT removal often pre-medicate with diphenhydramine (Benadryl) and famotidine (Pepcid) before cutting near these tumors. I’ve seen dogs come in for what looked like a routine lump removal and crash on the table because nobody prepped the surgical site properly. That’s not meant to scare you; it’s meant to underscore why this specific tumor type requires a vet who knows what they’re doing.
The degranulation risk also explains why you’ll sometimes hear “don’t manipulate the mass.” Repeatedly squeezing or pressing on an MCT can trigger granule release and cause localized swelling, redness, and a condition called Darier’s sign (a wheal-and-flare reaction). If you notice a lump suddenly doubling in size after your dog scratches at it or after you’ve been pressing on it, that’s a characteristic MCT behavior, not a coincidence.
Grading: The Number That Changes Everything
Helpful resource: Zesty Paws Hip and Joint Supplement Chews for Dogs is a top-rated option for this. (As an Amazon Associate this site earns from qualifying purchases.)
For a long time, the veterinary pathology world used a three-tier Patnaik grading system (Grade I, II, III). As of the past decade, a two-tier system proposed by Kiupel has become more common at academic centers and specialty practices. The two-tier system classifies MCTs as either low-grade or high-grade, and research has shown it’s actually more predictive of outcome than the older three-tier approach.
Here’s how prognosis breaks down in practical terms:
| Grade / Classification | Approximate Survival (No Metastasis at Dx) | Primary Treatment | Notes |
|---|---|---|---|
| Patnaik Grade I / Kiupel Low-Grade | >90% 2-year survival with clean margins | Surgery alone | Excellent prognosis if fully excised |
| Patnaik Grade II / Kiupel Low-Grade | 70-85% 2-year survival with clean margins | Surgery +/- adjuvant | Behavior is variable; some oncologists add chemo |
| Patnaik Grade II / Kiupel High-Grade | 40-60% 1-year survival | Surgery + chemo or targeted therapy | Aggressive staging recommended |
| Patnaik Grade III / Kiupel High-Grade | Median survival 4-6 months with treatment | Multimodal: surgery, chemo, Palladia | Poor prognosis; palliation often discussed |
| Any grade with lymph node involvement | Significantly reduced; case-dependent | Staging + systemic treatment | Lymph node biopsy changes the whole plan |
These are estimates drawn from published veterinary oncology literature, including work from the Veterinary Cancer Society. Individual cases vary widely. I don’t give people these numbers to depress them; I give them so they can have an informed conversation instead of nodding blankly at their vet.
Diagnosing It: What Should Actually Happen at Your Vet
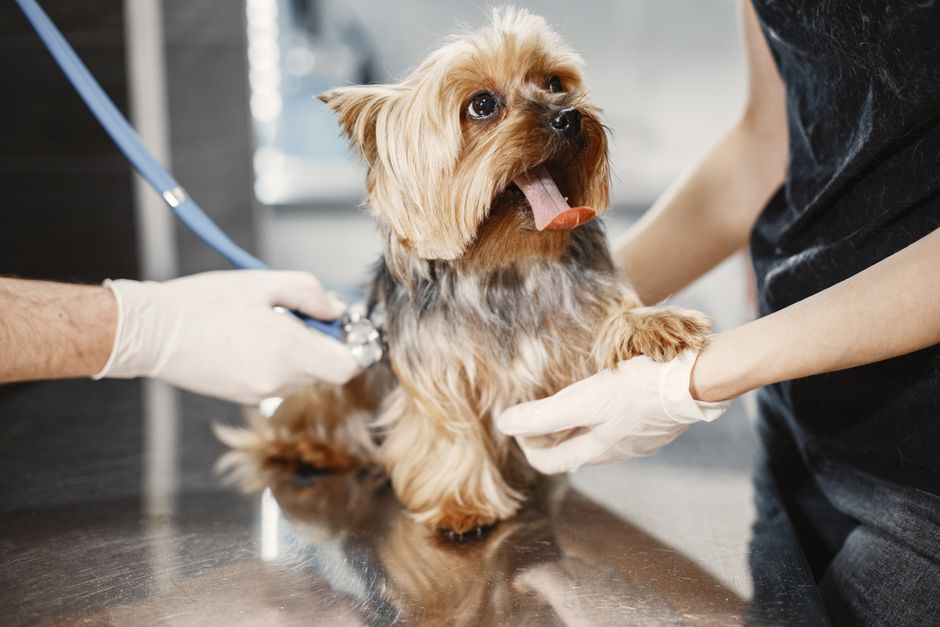
Fine needle aspirate (FNA) first. Your vet inserts a small needle into the mass, pulls back cells, and smears them on a slide. It takes about 90 seconds. Mast cells are visually distinctive under the microscope: large cells with purple granules. In my experience, a good in-house microscope can get you a strong suspicion same day. Definitive grading requires surgical biopsy and histopathology at an external lab, usually a 3-5 business day turnaround.
If your vet identifies an MCT (or suspects one), the next conversation should be about staging. Staging tells you whether the cancer has spread. At minimum, that means:
- Regional lymph node aspirate or biopsy
- Chest radiographs (looking for thoracic spread)
- Abdominal ultrasound (checking spleen and liver, both common sites of mast cell infiltration)
- Buffy coat analysis or bone marrow biopsy in high-grade cases
This is where costs start adding up. Staging workup at a general practice might run $400-$800. At a veterinary internal medicine or oncology specialist, factor in $1,200-$2,500 depending on what’s included. I know that feels like a lot before you’ve even started treatment. But incomplete staging means incomplete information, and that affects every treatment decision downstream.
A real-world example from my clinic: A 9-year-old Labrador came in with a 2 cm MCT on her thigh. Grade II Patnaik. Owner declined full staging due to cost, proceeded to surgery. Margins were clean. Six months later, a splenic mass. Retrospectively, the spleen was probably already involved at initial diagnosis. Full staging and earlier recognition of systemic disease might have changed the initial treatment plan. I can’t say it would have saved her, but it would have changed the conversation.
Treatment Options, Honestly Assessed
Surgery is the primary treatment for localized MCTs. “Wide margins” means the surgeon removes a substantial cuff of normal tissue around the tumor, often 2-3 cm laterally and one fascial plane deep. This sounds aggressive because it is. On the limbs or face, achieving wide margins isn’t always possible anatomically, and that incomplete excision scenario is where radiation therapy comes in.
Radiation works well for incompletely excised low- to intermediate-grade MCTs. Median survival times for dogs treated with surgery plus radiation for incomplete margins are genuinely comparable to those with clean surgical margins in some studies. The downside is cost ($6,000-$12,000 for a full radiation course at most specialty centers) and the need for general anesthesia at each fraction.
Toceranib phosphate, sold as Palladia by Zoetis, was the first FDA-approved targeted cancer therapy for dogs and it changed things meaningfully for inoperable or metastatic MCTs. It works by inhibiting KIT, a receptor tyrosine kinase that’s mutated in roughly 15-40% of canine MCTs. Tumors with KIT mutations (exon 11 or 12) tend to respond better to Palladia, though even KIT-wild-type tumors sometimes respond. As of July 2026, Palladia runs roughly $10-$16 per tablet depending on dose and pharmacy, and most dogs take it every other day. Monthly medication costs typically land between $300 and $600.
The research here is genuinely mixed on whether adding a tyrosine kinase inhibitor (TKI) before surgery to shrink a tumor actually improves long-term outcomes versus just going straight to surgery. It’s an active area of discussion in veterinary oncology. If your oncologist recommends neoadjuvant Palladia, ask specifically what the goal is: Is it to achieve resectability? Reduce surgical complexity? Make sure you understand the “why” before you start.
Prednisone is often used palliatively in cases where surgery and aggressive treatment aren’t possible or desired. It can temporarily reduce tumor size in some cases. It’s not a cure, and I’ll be honest: its role in MCT management as monotherapy is mostly about buying time and quality of life, not remission.
Breeds That Need Faster Action
Boxers, Boston Terriers, Pugs, Bulldogs, and Labrador Retrievers have documented genetic predisposition to MCTs. If you own one of these dogs, any new lump gets an FNA. Not “watch it for a month.” Not “it feels soft so it’s probably fine.” Same-day or next-appointment aspirate. Boxers in particular can develop multiple simultaneous MCTs, and some Boxer MCTs are histologically lower-grade despite appearing aggressive clinically.
Golden Retrievers are another breed where I’ve seen MCTs pop up more than expected, though the genetic link is less firmly established than in Boxers.
Signs That Mean “Go Today, Not Monday”
Rapid tumor growth over 48-72 hours, especially with surrounding swelling and redness, warrants a same-day call. A dog who is vomiting repeatedly alongside a skin mass, or showing signs of GI bleeding (dark, tarry stools), could be experiencing systemic effects of tumor degranulation. The ASPCA Poison Control Center has a 24-hour line if you’re unsure whether a symptom warrants emergency care, though for active GI bleeding you should go directly to an emergency vet.
For any dog already diagnosed with MCT who develops facial swelling or difficulty breathing, that’s an emergency. Go now.
Practical Costs in 2026
These are midpoint estimates. Geographic variation is real: a surgical excision in rural Montana is priced differently than the same procedure at a specialty center in Boston. These numbers are drawn from my own experience ordering procedures and talking to owners about invoices over 13 years. (AAHA-accredited hospitals may charge slightly more for MCT staging and surgery, but accreditation also correlates with better surgical and anesthetic protocols, which matters for this specific tumor type.)
A scenario I see regularly: Owner with a Grade II MCT diagnosis, $1,800 for surgery, margins came back “narrow but complete.” Oncologist recommends radiation as a precaution: $9,000 they don’t have. Decision: close monitoring with recheck every 8-12 weeks, and a plan to discuss Palladia if there’s any evidence of local recurrence. That’s a reasonable, informed choice. Not giving up; being strategic with real-world constraints.
Sources
- Kiupel M, et al. (2011): “Proposal of a 2-tier histologic grading system for canine cutaneous mast cell tumors to more accurately predict biological behavior.” Veterinary Pathology.
- Patnaik AK, et al. (1984): Original three-tier MCT grading system. Veterinary Pathology.
- Veterinary Cancer Society: Resources on staging, treatment protocols, and specialist referral guidance.
- London CA, et al. (2009): Clinical trial data for toceranib phosphate (Palladia) in canine MCT. Clinical Cancer Research.
- Welle MM, et al. (2008): “Canine mast cell tumours: a review of the pathogenesis, clinical features, pathology and treatment.” Veterinary Dermatology.
Photo: Tima Miroshnichenko via Pexels
This article is for general informational purposes only and does not constitute veterinary advice. Pet health symptoms can have many causes and require professional evaluation. Always consult a licensed veterinarian for diagnosis and treatment specific to your pet.
Recommended Resources
Disclosure: As an Amazon Associate, we earn a small commission from qualifying purchases at no extra cost to you. We only recommend products that genuinely support the topics covered in this article.
- EVERLIT 95-Piece Vet-Approved Pet First Aid Kit (~$32), Vet-approved 95-piece kit for dogs and cats, covers cuts, burns, sprains, and emergencies until you can reach a vet.
- Nutramax Cosequin DS Joint Supplement for Dogs (132ct) (~$36), The #1 veterinarian-recommended joint supplement brand, clinically studied for reducing joint pain in dogs.